
 TR
 EN
 RU
Recipient Information Guide
Organ transplantation is today regarded as a routine, established and advanced treatment method applied in many chronic organ diseases.
Liver transplantation can be performed in two ways:
• Deceased-donor liver transplantation
• Living-donor liver transplantation
Liver transplantation from living persons is carried out by transplanting a part of the donor's liver in a way that does not put the donor's life at risk.
Kent Hospital, which supports organ donation, treats patients with social security coverage at its SGK-contracted Liver Transplant Center with the comfort of a private hospital.
The Kent Hospital Liver Transplant Team has specialized in liver transplantation for 10 years and has so far performed liver transplants on nearly 1000 patients.
If you apply to our center for a liver transplant, your pre-operative tests are completed within a very short time, and all hospital staff help you regain your health without waiting in line.
ABOUT YOUR LIVER
The liver, the largest and most important solid organ of the body, has many vital functions, each more important than the next. Of its countless functions, 4 are especially important.
1. Selecting and storing the substances the body needs from the food we eat, and producing the proteins required to maintain the normal cycle of life
2. Producing the bile acid required for digesting food and delivering it to the digestive system
3. Clearing the body of harmful substances produced by other systems
4. Producing the factors needed to fight infection and to stop bleeding occurring anywhere in our body
WHAT IS LIVING-DONOR LIVER TRANSPLANTATION?
Living-donor liver transplantation is a complex surgical procedure in which a part of the liver taken from a living donor (provided that enough liver remains for the living donor) is placed into the recipient.
WHY ARE ORGAN TRANSPLANTATION AND LIVING DONORS NEEDED?
There are thousands of patients on the National Organ Waiting List who have been diagnosed with end-stage liver failure and are waiting for a liver transplant. Unfortunately, there are not enough organs for all patients.
According to June 2006 UNOS (American National Waiting List) data, while 17,645 patients were waiting for a transplant, only 6,000 of them were able to receive one. About 50% of the patients on the waiting list die while waiting for an organ transplant, while new patients are added to the list every day. With living donors, the organ shortage and death rates can be reduced.
WHAT ARE THE ADVANTAGES OF LIVING-DONOR LIVER TRANSPLANTATION?
• Short waiting time: Loss of patients while on the waiting list is reduced, and the most favorable conditions can be provided for the recipient to undergo surgery.
• It makes it possible to transplant the most suitable organ.
• Being able to perform the surgical procedures under elective conditions allows the success rate of the transplant to be kept at its highest level.
For patients who develop end-stage liver failure, the average one-year chance of survival is around 50%, and with the complications that develop, this rate can fall even lower. It has been shown that the worse the condition in which patients are transplanted, the shorter their survival and the more difficult their post-operative period. For this reason, appropriate timing and appropriate patient selection become even more important in achieving encouraging results.
BASIC PRINCIPLES
• The transplant candidate must accept living-donor liver transplantation.
• Every recipient for whom donor preparation has begun is also registered on the deceased-donor waiting list. Preparing a living donor does not affect the recipient's position on the deceased-donor list. Organs obtained from deceased donors are offered according to the recipient's priority on the National Organ Transplant Waiting List, regardless of whether the recipient has a potential living donor.
• Donors must be people aged between 19 and 50 (having reached the age of 18), of sound mind and without any health problems.
Important to remember!
The main motivation of donors is the desire to help the recipient. For this reason, donors must make their decisions of their own free will, free from outside pressure, coercion, threats or any other insistence.
During the evaluation, donor safety is the most important consideration for the entire transplant team. If, during the clinical examination and laboratory tests carried out by the transplant team on a potential donor candidate, any finding is encountered suggesting that harm could come to them, the tests are stopped at that stage. The preparation period can take days, weeks and sometimes months, depending on the donor's state of health and the urgency of the recipient.
If there is more than one donor candidate, the candidates are ranked in light of the clinical examinations and laboratory tests, and testing begins with the most suitable candidate. Our main aim is for the donor to trust the team, to ask every question on their mind and to receive answers to them. All information obtained during the evaluation is kept strictly secure and will not be shared with any third parties.
All expenses of the donor related to living-donor liver transplantation are paid by the recipient's healthcare institution. This includes all pre-transplant tests of the recipient and the donor, and all examinations and treatments carried out during the hospital stay, with the surgical fee included. For check-ups and tests to be carried out on the donor after discharge, the donor's own social security coverage applies.
According to the regulation that entered into force with the approval of the Turkish Ministry of Health dated 28.06.2004 and numbered 4690, organ and tissue transplantation from a living person may be performed from the recipient's blood relatives and relatives by marriage up to the fourth degree (including the fourth degree).
Regarding the fourth degree of kinship, Article 17 of the Turkish Civil Code states: “The degree of kinship by blood is determined by the number of births linking the relatives to one another.”
Accordingly, in kinship by blood, according to a person's degrees of relationship:
1st-degree relatives: mother, father and child
2nd-degree relatives: sibling, grandfather, grandmother, grandchild
3rd-degree relatives: paternal uncle, paternal aunt, maternal uncle, maternal aunt, nephew/niece (a sibling's child)
4th-degree relatives: the children of those in the 3rd degree.
In kinship by marriage, the relatives on the spouse's side are graded in the same way.
When deciding to accept or reject a potential donor candidate, the doctors and members of the transplant team also take their own ethical and moral responsibilities into account. The transplant team is under no obligation to perform every living-donor surgery. In unusual ethical matters, the recommendations of the Transplant Ethics Committee are also sought.
Only 20% of the candidates who apply to become liver donors pass all the steps and become living donors.
The most common reasons for not proceeding with surgery are: unsuitable vascular anatomy, abnormal blood tests, and medical problems that had not previously been identified and are detected at that time.
Donor candidates have the right to withdraw from volunteering at any time, deciding after preparation has begun that living donation is not suitable for them.
Donor candidates and their decisions are always respected, and they are supported to the end. Unless the donor specifically requests it, no information is given to recipients, and every effort is made to protect donor safety at the highest level. Donor candidates should contact us directly with all their questions and concerns about every stage. Information about the donor will never be given to third parties (family members, friends, recipients, etc.).
If you would like to speak with a patient who has undergone living-donor liver transplantation or with their donor, we will be happy to help you with this.
WHAT ARE EMERGENCY SITUATIONS? DOES THE RISK INCREASE?
Emergency living-donor liver transplantation comes into question only in exceptional circumstances, usually in adults who develop acute liver failure that can result in death within a few days, or in children whose liver function is deteriorating rapidly. Potential donors must have clearly understood and accepted that transplants performed in emergencies may carry significantly higher risks than transplants performed under so-called “elective” conditions, in which all circumstances are optimal. (For example: increased pneumonia – lung infection – because there was not enough time to quit smoking, or increased blood clotting problems because birth control pills were not stopped in good time…)
WHO CAN BE A DONOR? WHAT ARE THE REQUIREMENTS FOR BEING A DONOR?
First of all, people who are compatible with the patient in blood group and who are related to the patient or have an emotional bond with them in some way can be donors. Because the donor candidate will face a major surgical operation, they undergo a series of health checks. The donor must be completely healthy.
WHAT QUALITIES ARE SOUGHT IN A POTENTIAL DONOR CANDIDATE?
Voluntariness Is the Essential Element!
• The recipient and the donor must have compatible blood groups. (See the table.) • Rh factor compatibility is not required for the donor candidate.
• They must not have any physical or mental problems.
• Candidates must be between 19 and 50 years old.
• Donors must be within the normal or near-normal range on the body mass index chart.
ARE THERE FACTORS THAT PREVENT SOMEONE FROM BEING A DONOR? IF SO, WHAT ARE THEY?
• People with hepatitis B or C • Substance addiction such as alcohol and drugs
• HIV infection
• People with cancer
• People with a psychological illness that has not been treated or cannot be treated
• Unusual vascular pathologies (that make surgery impossible)
• DM (diabetes mellitus), HT (hypertension)
HOW IS DONOR PREPARATION DONE? WHAT STEPS MUST A DONOR CANDIDATE GO THROUGH?
STEP 1: MEETING AND CLINICAL EXAMINATION This is carried out by a doctor from the organ transplant team meeting the donor candidate.
STEP 2: BLOOD TESTS AND ORGAN FUNCTION TESTS The blood tests include liver function tests, kidney function tests, blood counts, and blood tests looking for diseases that may be present (for example hepatitis, cancer, etc.). A chest X-ray (PA - lateral) and an electrocardiogram (ECG) are taken if the candidate is over 45. Because these values are normal, the donor candidate is taken into evaluation.
STEP 3: CONSULTATIONS At first, consultations are requested from the psychology, internal medicine, cardiology and chest diseases departments and, for women if deemed necessary, from the obstetrics and gynecology outpatient clinics.
Candidates in whom no problem is found in these 3 steps move on to step 4.
STEP 4: RADIOLOGICAL IMAGING METHODS A special computed tomography scan is performed on the donor candidate. With the computed tomography, the person's liver volume is calculated. For a donor candidate to be accepted, the amount of liver remaining after the surgery must be sufficient for their later life, and at the same time the amount of liver they will give to their relative must be sufficient for the recipient.
STEP 5: ADDITIONAL PROCEDURES If deemed necessary after all these tests and imaging, a liver biopsy is performed. With the biopsy, criteria such as any fatty change in the liver are evaluated.
STEP 6: THE MOMENT OF DECISION Finally, following a council held by the doctors of the organ transplant team, if the donor candidate is accepted, the day of the operation is decided.
WHAT HAPPENS THE NIGHT BEFORE THE OPERATION?
• Fasting: The patient is kept fasting after midnight (24:00). From that time on, the patient is not allowed to eat or drink anything. (Complete fast)
• Shaving: The area from below the chest down to above the knees is shaved.
• Bathing: After shaving, the patient is bathed with chlorhexidine solution. (The body is washed from the neck down.)
• In the morning the patient is dressed in an operating gown.
• After that, both the donor and the recipient are taken to the operating room.
Note:
• Alcohol must be stopped at least 4 weeks before surgery.
• Smoking must be stopped at least 2 weeks before surgery.
• Birth control pills must be stopped at least 4 weeks before surgery.
WILL I RECEIVE BLOOD DURING THE OPERATION?
The answer is most likely no. Our hospital secures sufficient blood for patients from the Turkish Red Crescent (Kızılay).
Donors are asked to be at the hospital one day beforehand. They are prepared for the operation the next day.
During the operation, the bile ducts and vascular structures are carefully examined with the help of ultrasonography and cholangiography. After the gallbladder is removed, the surgeon exposes the feeding veins and bile ducts of the part of the liver that will be taken (see the diagram on the back page).
In some cases, abnormalities of the blood vessels or bile ducts that endanger the donor's life, and that could not be detected despite detailed tests before surgery, may be found during the operation. If such a situation is encountered, the donor operation is stopped. This situation occurs in about 1–2% of cases.
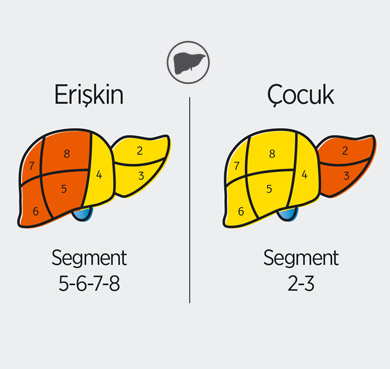
FOR ADULT RECIPIENTS, FROM THE DONOR
The right lobe of the liver, labeled 5, 6, 7, 8 in the figure, is taken.
FOR INFANT RECIPIENTS
The left lateral segment of the liver, labeled 2, 3 in the figure, is taken.
FOR CHILDREN AND ADULTS
The left lobe of the liver, labeled 2, 3, 4 in the figure, is taken.
THE OPERATION
TAKES ABOUT 4–6 HOURS FOR THE DONOR
AND 8–10 HOURS FOR THE RECIPIENT.
ARE THERE POTENTIAL RISKS OF LIVING-DONOR LIVER TRANSPLANTATION?
Provided that it is performed by a qualified and experienced team, donor surgery carries no different risk from other operations. However, recipients and donors must be well informed about the benefits and drawbacks of recipient and donor surgery and about the problems that may arise from the operation. During the pre-operative checks, the surgeon shares this information with the recipient and the donor. The recipient and donor should feel at ease during these discussions and should be sure to ask the team any questions that come to mind.
As in any operation performed under general anesthesia, events affecting the cardiovascular system (arrhythmia, etc.) and the respiratory system (pneumonia, etc.), referred to as complications, may develop. The living-donor team will explain these to you in detail.
Some of these complications are:
• Anaphylactic (allergic) reaction to anesthesia and blood products
• Heart attack at any point during the operation
• Pulmonary embolism
• Fluid accumulation in the lungs
• Fluid accumulation throughout the body (edema)
• Infection
Although the rate of complications related to the donor operation is minimal, the main complications are:
• For a living donor there is a 1% risk of death.
• For those who give the right lobe of the liver, the risk of death is twice as high as for those who give the left lobe or left lateral segment.
• Incompatibility between the transplanted organ and the recipient's tissues
• Psychological trauma (if the recipient is lost). For the recipient there is a risk of death of around 10%.
• Incisional hernia (hernia at the wound site in the abdomen)
• Digestive complaints (indigestion, constipation, nausea, etc.)
• Bleeding
• Bile leakage from the remaining liver part
• Temporary jaundice
• Permanent scar
WHAT ARE THE COMPLICATION RATES?
DONOR SURGERY
The operation lasts about 4 to 6 hours on average. On average, 1 or 2 units of blood are needed during the operation. A complication that may be seen in the early period is atelectasis. The most common complications and their rates are:
• Rate of return to the operating room because of bleeding after the operation: 3%
• Rate of bile leakage that can be treated endoscopically: 1.8%
• Rate of intra-abdominal collection requiring drainage: 3.6%
• Rate of pulmonary embolism: 1.8%
• Rate of surgery for a hernia developing at the incision site: 2.2%
WHAT HAPPENS AFTER THE OPERATION?
After the operation, donors are monitored in the operating-room intensive care unit. They are usually moved to a standard ward room on the 2nd or 3rd day. A ban on visitors is unavoidable. Any infection coming from outside can create life-threatening problems for a donor who has undergone major surgery.
For the first 24 hours donors are kept on absolute bed rest (this can sometimes extend to 48 hours). During this time the donor must not get out of bed in any way, and must not even raise their head.
The main problems encountered in this period are pain at the surgical site and back pain. When you have pain, please do not hesitate to report it; it will be treated immediately. Loss of appetite, nausea and a sensation of bad smells in the period after surgery are complaints that occur after most liver operations. Please report any such complaints to the relevant team.
When you wake up you will have a urinary catheter so that you can empty your bladder, and there will also be 1 or 2 thin tubes (drains) at the surgical site. These are placed to remove fluids that collect inside during and after the operation, and they will be removed when the amount of fluid draining out decreases.
Every treatment and procedure performed on you will be carried out by the experienced doctors and nurses who make up the organ transplant team. Please do not worry about this.
You will be discharged after a follow-up period of about 1 week to 10 days. During this period, all of your treatment and follow-up will be carried out daily by the living-donor team. If, after the blood tests and other follow-up checks, there is no problem, you can be discharged.
FREQUENTLY ASKED QUESTIONS
1 - How much of my liver will be removed?
The part to be removed and its proportion will be determined after computed tomography. However, there are two important concepts. The first is that the remaining liver volume must be enough not to threaten the donor's life, in other words, enough to meet the donor's own needs. The other requirement is that a piece of liver large enough to meet the recipient's needs must be taken. These two factors are evaluated together by the whole transplant team in a council, and a decision is made without putting the donor or the recipient at risk.
In summary, about 50–60% of the liver is taken from a donor candidate who will give part of the liver to an adult recipient. Depending on the structure of the right lobe, this proportion can rise to 70%. From the donor of an infant or a very low-weight recipient, about 20% of the liver is taken.
2 - Will the remaining part of my liver be enough for me? Will the remaining liver be as large as before?
The remaining part of the liver is sufficient for a healthy person without endangering their life. The liver reaches roughly its former size at the end of a period of about 3 months. However, the fastest growth takes place within the first 10 days after surgery.
3 – How long will it take before I can return to my work and normal life?
While the liver is regaining its former size, because of the energy it uses and the demands placed on it, it is entirely natural to feel tired during the first 3 months after surgery.
For this reason, it should be known that donor candidates who work in heavy jobs or jobs that rely on physical activity can return to these jobs in 5–6 months at the earliest, while those with desk jobs can return to them within 3–4 months. Especially during the first 6 months, they must not lift weights of more than 2–3 kg. This is absolutely necessary both because of the link with bodily fatigue and to protect against hernias that may form at the surgical site. Apart from this, you can comfortably manage your daily activities yourself at about the end of the 1st month.
4 - When will my skin stitches be removed?
The time of stitch removal depends on wound healing. After the skin stitches are checked by the donor team, if wound healing is complete, they are removed at the time of your discharge or within the period you are told. (Usually 15 days after the date of surgery)
5 - When can I bathe?
After you are discharged you can bathe in the manner of a shower (so that cleansing solutions do not come into contact with the wound).
6 - Until when do I need to have dressings done?
After discharge you do not need to have dressings done unless the organ transplant team tells you otherwise.
7 - Will I have any restrictions regarding food?
In the period after surgery, especially within the first 2 weeks, you may have complaints such as loss of appetite, a sensation of bad smells or nausea. After your discharge you have no very strict restrictions on food. However, especially within the first 2 weeks, we recommend that you eat foods that do not cause gas and are easily digested. In particular, we do not recommend legumes (dried beans, chickpeas, etc.) or excessively fatty food prepared outside the home (lahmacun, fatty kebab, etc.) in the first 15 days. In addition, there is no restriction on foods containing carbohydrates and sugar, as long as you do not overdo it. Because excessive weight gain in the long term will cause problems, care should be taken in this regard and weight checks should be done at intervals.
8 - When can I travel?
There is no objection to your traveling 1 week after discharge.
9 - Is there any medication I need to take continuously?
Apart from taking vitamins and a stomach protector for a period (about 3 months) to increase your body's resistance, there is no medication you need to take continuously. However, within the first year, if you need to take a special medication for other reasons, or if surgery is under consideration, you must be sure to consult the LIVER DONOR TEAM.
10 - Is the gallbladder removed during surgery? Is there a possibility that this will cause me a problem in the future?
In liver transplantation for an adult recipient, the gallbladder is removed in order to expose the bile ducts. However, in donor operations performed for infants or small children, the gallbladder is not removed unless it is truly necessary. Removal of the gallbladder cannot cause you any problem.
11 - When can I start work?
About 3 months after surgery you can return to active life. However, during these first 3 months you should not take on a heavy workload.
12 - Do I need to use an abdominal corset?
To minimize the possibility of a hernia, we recommend that you use an abdominal corset during the first 3 months.
13 - Will I have check-ups?
If there is no problem after your discharge, your routine check-ups will be carried out at the Organ Transplant Outpatient Clinic in the 1st and 3rd months.
14 - What tests will be done at my check-ups?
Blood tests are done in the 1st month. An ultrasound is done in the 3rd month. Apart from this, you can come for a check-up at any time if you have any complaint.
